The Long Road to a Trial: Britain’s CRISPR Geography and the Patients Beyond the South East

In 2026, Britain’s most advanced gene-editing trials are still easier to reach from a London postcode than from much of the country. The pattern is familiar in clinical research: specialist hospitals, research nursing teams, pharmacy capacity and laboratory infrastructure tend to gather in the same few places. For CRISPR, that geography matters more than usual. These are not always short studies with a handful of visits. Some require repeated blood tests, imaging, long follow-up and rapid access to a specialist team if something goes wrong.
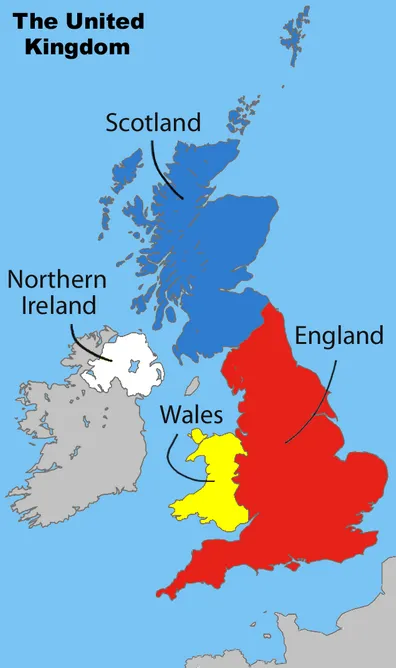
The result is a practical inequality that sits beneath the science. A patient in Cardiff, Glasgow, Belfast or Carlisle may be medically eligible for a trial and still find that participation is difficult to sustain. The question is not whether London should host advanced research. It is how the rest of the UK can take part without carrying an unreasonable burden.
Why the cluster forms
CRISPR trials need more than a willing clinician. They need a site with staff trained in advanced therapies, a pharmacy able to handle investigational products, laboratories that can process samples to a strict timetable, and imaging or clinical facilities available at short notice. They also need enough patients to make recruitment viable and a research culture that can move quickly when a protocol changes.
London and the South East have accumulated those advantages over many years. Large teaching hospitals, biomedical research centres and specialist services are close together. Sponsors and contract research organisations often prefer sites with a proven record, because opening a new site takes time and money. That is a rational choice for a trial, but it reinforces the map.
The effect is not confined to CRISPR. It applies across cell and gene therapies. What makes gene editing distinctive is the length and intensity of some follow-up. A trial may ask patients to return for monitoring at fixed intervals, sometimes for years. Travel is not a one-off inconvenience; it becomes part of the treatment schedule.
The burden beyond the South East
For patients in northern England, Wales, Scotland and Northern Ireland, the first obstacle is often referral. Not every clinician will know which CRISPR trial is open, which site is recruiting, or whether a patient meets the inclusion criteria. NHS genomic medicine centres can help, but referral routes are not uniform across the four nations. A patient in England may be referred through a specialist genomics service; a patient in Scotland, Wales or Northern Ireland may encounter a different pathway, different commissioning arrangements and different travel realities.
Then comes the practical arithmetic. A return journey to London from parts of Wales or the north of England can take a full day. From Belfast or the Highlands, it may require an overnight stay. Repeated visits can mean lost wages, childcare costs, hotel bills and time away from caring responsibilities. Trial budgets do not always cover these costs, and reimbursement rules vary.
There is also the question of shared care. A patient may be willing to travel for the trial itself but need routine monitoring closer to home. That requires clear communication between the trial team and the local hospital. Without it, patients can become the messengers, carrying results and instructions between services that should be talking to each other.
What regional patients should ask
Before agreeing to take part, patients and their clinicians should establish a few practical facts. The first is the follow-up schedule. How many visits are required in the first year? Which of them must take place at the trial site, and which could be done locally or remotely? A trial that looks manageable in a consent form can feel very different once travel is added.
The second is cost. Ask directly whether travel, accommodation and subsistence are reimbursed, and how quickly. Ask whether a companion can be reimbursed. Ask what happens if a visit is delayed by weather, strike action or transport disruption. These are not trivial questions; they determine whether participation is realistic.
The third is the emergency route. If a patient develops a fever or another concerning symptom between visits, where should they go? A local emergency department may not have the trial protocol or know the investigational product. The trial team should provide a clear, written plan and a contact number that works out of hours.
The referral conversation
Clinicians outside the South East also need better support. A general practitioner or district general hospital consultant may see a patient who could be eligible for a CRISPR trial but may not know how to start the conversation. NHS genomic medicine centres are an obvious route, but they are not a universal front door. Research networks, disease-specific charities and specialist societies can help fill the gap.
The conversation should begin early. Patients who might later need a trial should not first hear about it when they are already exhausted by standard treatment. A timely referral can allow time to arrange travel, discuss work commitments and identify a local clinician who can share monitoring.
A national problem, not a London one
It would be easy to frame this as a complaint about London. That would miss the point. The concentration of expertise is an asset for UK science, and many patients are willing to travel for a chance to take part. The problem is that the system has not yet built the supporting infrastructure to match the science. Travel advice, reimbursement, shared-care agreements and regional referral routes are not glamorous, but they determine who can say yes.
In 2026, Britain’s CRISPR trial map is still shaped by history and infrastructure. Changing it will take time. In the meantime, patients outside the South East deserve honest answers about distance, cost and follow-up before they sign a consent form. A trial should be a scientific opportunity, not a test of endurance.