Beyond the Final Visit: Britain's Unfinished Business in CRISPR Aftercare

Photo: DFID - UK Department for International Development, CC BY 2.0, via Wikimedia Commons
When a gene-editing trial closes its books, the biology does not switch off with the lights. A participant who received a single infusion of edited blood stem cells, or one dose of a lipid nanoparticle carrying an editor, may still be carrying edited cells years later. The trial itself, however, was designed around a timetable: screening, dosing, twelve months of scheduled visits, a final assessment. Once that timetable is exhausted, the scaffolding that supported the patient is quietly dismantled.
This mismatch — between a permanent intervention and a finite study — is what clinicians and patient organisations have begun to call the aftercare gap. It is not a scandal, and it is not unique to CRISPR. But as more British gene-editing programmes move from early-phase studies into later-stage trials, the gap is widening, and the people standing on the far side of it are patients who consented to something genuinely novel.
What the end of a trial actually means
Under UK clinical trials regulation, a study does not simply stop. Sponsors must notify the regulator when a trial concludes, publish a summary of results within a set period, and ensure that participants are told what was found. The 2024 revisions to the Medicines for Human Use (Clinical Trials) Regulations, in force since last year, tidied some of this machinery and strengthened transparency expectations.
What the rules do not do is create a continuing duty of care that follows the participant indefinitely. Once the trial ends, responsibility for a patient's health usually returns to the NHS — and the NHS consultant now holding the notes may never have seen a gene-edited patient before. In practice, many trial centres try to keep alumni under informal review, but informal arrangements depend on goodwill, on a funded research nurse, and on the sponsor still having an interest in the data.
The fifteen-year question
Regulators in Europe and the UK have long taken the view that gene therapies warrant extended observation, with follow-up periods of up to fifteen years for products that integrate into the genome or edit it. The logic is straightforward: an off-target edit or an unexpected clonal expansion might not announce itself in the first year.
In commercial programmes, that obligation sits with the marketing authorisation holder, which is expected to maintain a registry and report periodically. In investigator-led academic studies — a large share of UK gene-editing work — the position is murkier. Follow-up is typically discharged through annual questionnaires, occasional blood sampling and enrolment in a registry, but registries require staff, governance and secure data handling. When a grant ends, those things tend to end with it.
The uncomfortable consequence is that the long-term safety evidence on which future commissioning decisions rest is being generated, in some cases, by arrangements that no one has clearly agreed to fund.
Who pays, and who travels
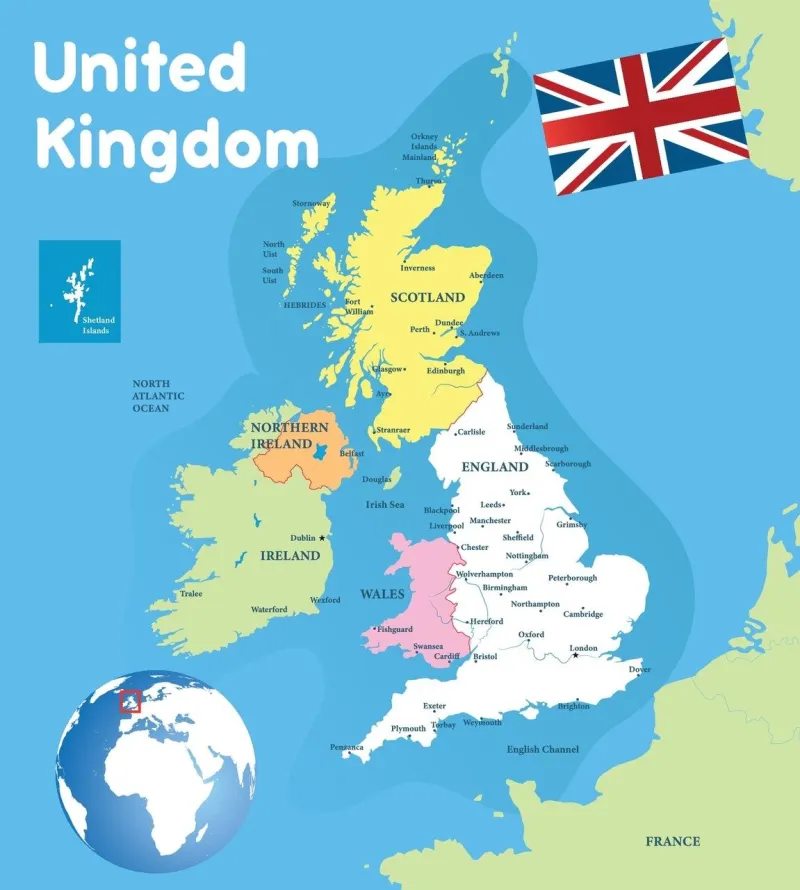
Britain's gene-editing trial capacity is concentrated. London, through Great Ormond Street and University College London Hospitals, hosts much of the paediatric and haematology activity; Manchester, Birmingham, Newcastle and Bristol hold significant advanced-therapy infrastructure, some of it built through the Advanced Therapy Treatment Centre network. For a family in Cornwall or Cumbria, a trial centred in one of those cities is not a short journey.
During a study, travel is often reimbursed from research funds, and NIHR-supported infrastructure absorbs some of the cost of the visits. After the study, those routes close. Routine NHS care does not normally pay for a patient to travel to a specialist centre for monitoring that is not part of their clinical treatment plan, and local services may not feel equipped to run assays that were, until recently, performed only in a research laboratory.
There is a further asymmetry. Much of the most valuable follow-up data — whole-genome sequencing to hunt for off-target edits, for instance — is research-grade rather than clinically indicated. Asking the NHS to fund it is difficult; asking a former participant to pay is worse.
Consent, data and the long tail
Consent forms for gene-editing trials increasingly include clauses covering long-term follow-up and secondary research use, and UK GDPR gives participants a right to withdraw. Those two things sit in tension. A patient who moves house, changes GP or simply stops responding to letters can drop out of a registry without anyone recording a decision, and the resulting gaps in the dataset are rarely random — they correlate with disadvantage.
Sponsors and registry custodians also face a practical question about linkage: whether follow-up data can be matched against national health records to detect late events such as malignancies or new diagnoses. Such linkage is possible, but it requires legal basis, transparency and public confidence, none of which is helped when patients first learn about it after the fact.
A checklist for anyone weighing up a CRISPR trial
Patients considering enrolment are entitled to clear answers before signing, and to have them in writing. The following questions are a reasonable starting point.
- How long does follow-up last, and how does the burden change between year one and year ten?
- Which named clinician, at which hospital, is responsible for my care once the trial closes?
- Who holds the long-term follow-up obligation — the sponsor, a company, or a registry — and what happens if that organisation ceases to exist?
- Will travel and time off work be reimbursed, and does that commitment extend beyond the trial period?
- What is the plan if I move to another region, or abroad?
- Will I be told the trial results, in what form, and when?
- What data will be held about me, who can access it, and how would I withdraw?
- If a late effect emerges, which team investigates it, and who decides whether it is related to the treatment?
The stakes for the NHS
Aftercare is not an administrative footnote. For one-shot therapies, it is the price of the cure. NHS England's specialised commissioning and NICE's appraisal routes for advanced therapies both depend on evidence about durability and late harms, and that evidence is generated by the very follow-up arrangements currently left to chance.
A workable model probably needs three things: a properly funded national registry for patients who have received genome-editing products; a named clinical contact written into every consent form; and a transition plan agreed with local services before the final study visit rather than after it. None of that is glamorous, and none of it will make a headline. But without it, the UK will accumulate a cohort of patients who received extraordinary medicine and then, at the moment the science became most interesting, stopped being counted.